Loading subject page…


53,517 views

Video Summary: Myasthenia Gravis Overview and Treatment Explained
Did you know that some patients at Johns Hopkins Hospital wake up unable to lift their eyelids, yet by evening can see clearly again? This fluctuating muscle weakness characterizes myasthenia gravis overview treatment, an autoimmune condition where the body's immune system mistakenly attacks communication between nerves and muscles. The myasthenia gravis overview and treatment explained in medical literature shows how antibodies block acetylcholine receptors at neuromuscular junctions, leading to progressive muscle fatigue that can affect everything from facial expressions to breathing. Watch the full video on JoVE Coach to master this concept with expert-led visuals and step-by-step explanations.
Myasthenia gravis represents one of the most well-characterized autoimmune neuromuscular disorders, affecting approximately 20 per 100,000 Americans according to the Myasthenia Gravis Foundation of America. This condition exemplifies how autoimmune mechanisms can specifically target neuromuscular transmission, making it a crucial topic for AP Biology students studying immune system dysfunction and for pre-med students preparing for the MCAT.
The disease mechanism centers on antibodies directed against the alpha-1 subunit of nicotinic acetylcholine receptors at the neuromuscular junction. These pathogenic antibodies employ three distinct mechanisms to disrupt normal neurotransmission. First, they directly compete with acetylcholine for binding sites, effectively blocking normal receptor activation. Second, they cross-link adjacent receptors, triggering internalization and degradation of functional receptor complexes. Third, they activate complement cascades that cause postsynaptic membrane lysis, permanently reducing receptor density.
At Harvard Medical School and other leading institutions, students learn that this receptor loss creates a unique clinical picture where repeated muscle stimulation leads to progressive weakness-a phenomenon easily demonstrated in clinical examinations through sustained upward gaze testing.
The characteristic symptom progression follows a predictable anatomical pattern that medical students at institutions like Stanford and UCLA must master for clinical rotations. Initial symptoms typically involve extraocular muscles, causing ptosis (drooping eyelids) and diplopia (double vision). Patients often report that symptoms worsen throughout the day-a hallmark feature distinguishing myasthenia gravis from other neuromuscular conditions.
As the disease progresses, bulbar muscles become affected, leading to dysarthria (slurred speech) and dysphagia (difficulty swallowing). The Mayo Clinic reports that approximately 85% of patients eventually develop generalized weakness affecting limbs and, most critically, respiratory muscles. This progression pattern frequently appears in USMLE Step 1 questions, where students must differentiate myasthenia gravis from conditions like Lambert-Eaton syndrome or botulism.
Modern treatment approaches target different aspects of the autoimmune process. Anticholinesterase medications like pyridostigmine work by inhibiting acetylcholinesterase, allowing acetylcholine to accumulate at synapses and improving the probability of successful neurotransmission despite reduced receptor numbers. This symptomatic treatment provides immediate relief but doesn't address underlying autoimmune mechanisms.
Immunosuppressive therapies form the cornerstone of long-term management. Corticosteroids like prednisone suppress antibody production, while agents such as azathioprine and mycophenolate provide steroid-sparing immunosuppression. Plasmapheresis offers rapid improvement by physically removing circulating antibodies-particularly valuable during myasthenic crises treated at centers like the Cleveland Clinic.
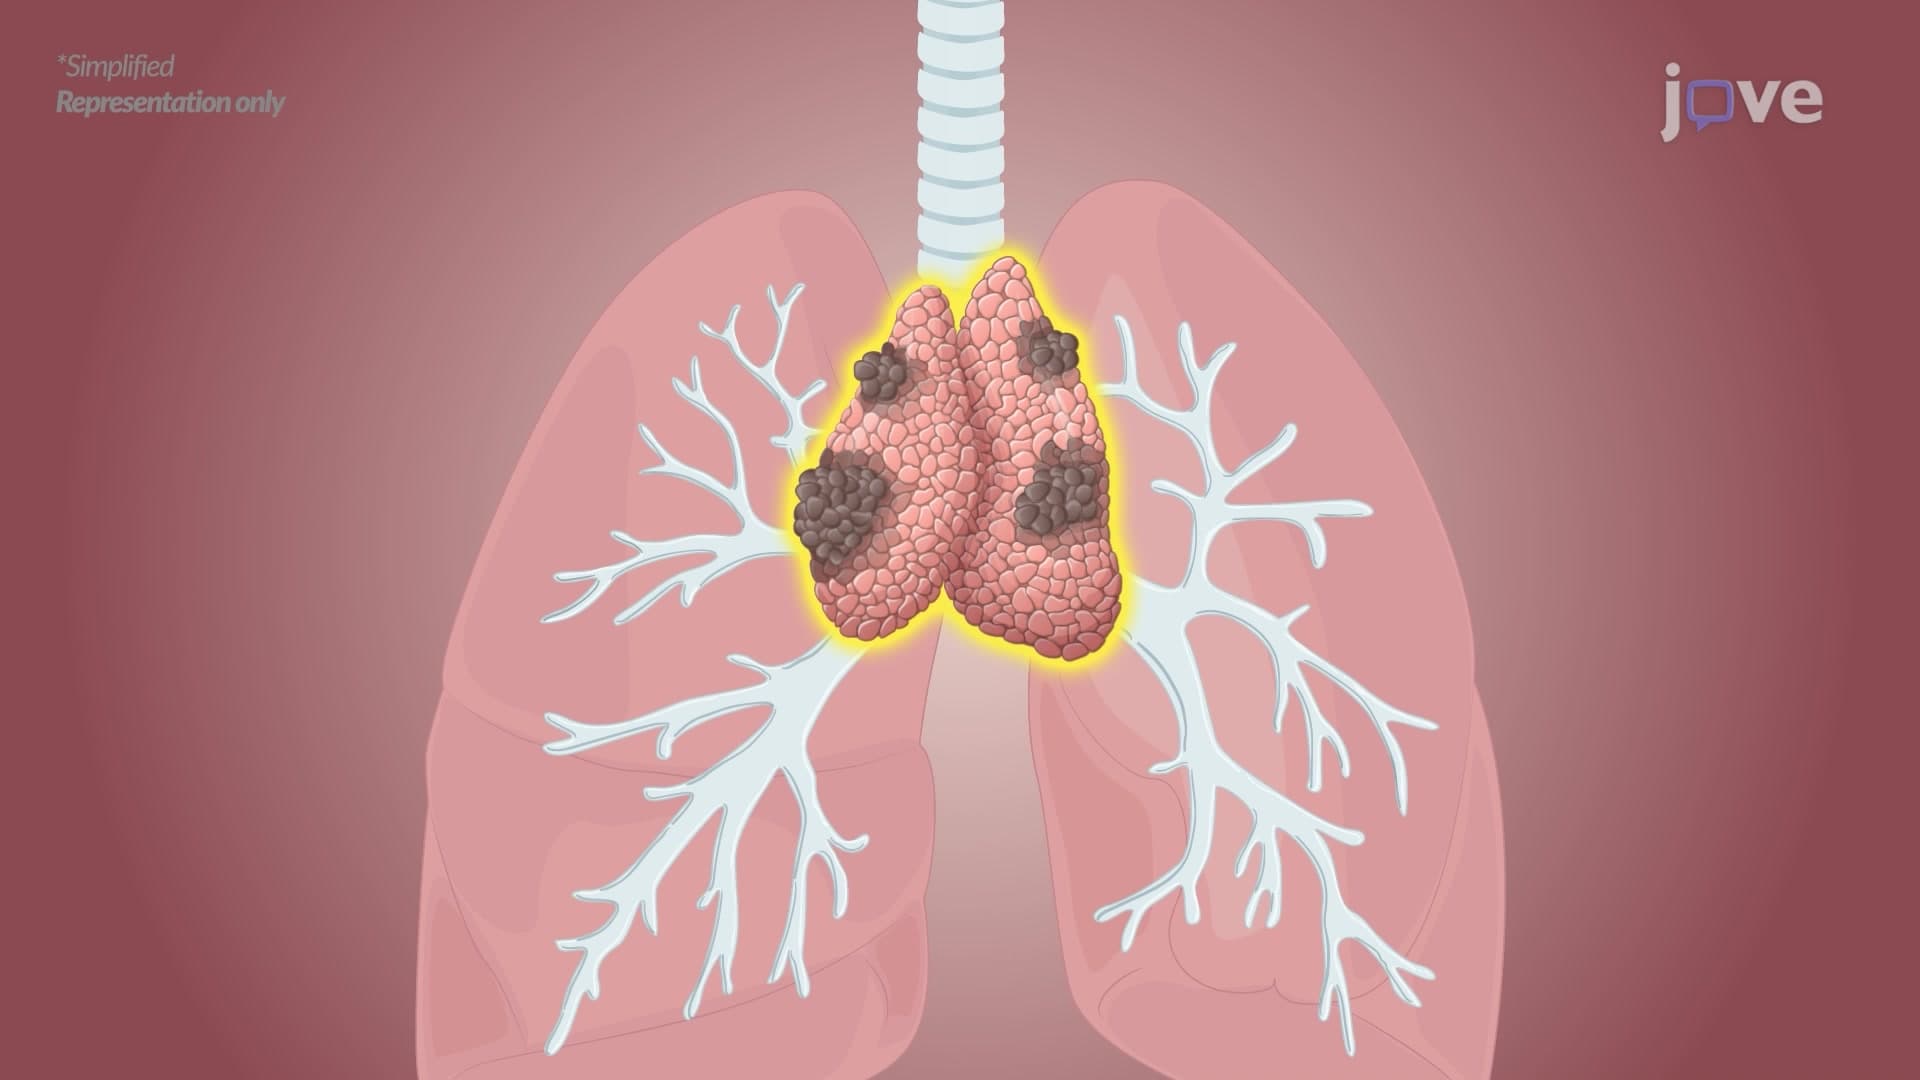
Thymectomy represents a unique therapeutic intervention, as approximately 75% of myasthenia gravis patients have thymic abnormalities. Even in patients without detectable thymomas, surgical removal of the thymus gland can lead to sustained remission, suggesting the thymus plays a central role in perpetuating the autoimmune response.
Related Micro-courses