Loading subject page…


11,199 views

Video Summary: Assessment Gastrointestinal System I Subjective Data Explained
Did you know that up to 70% of Americans experience digestive symptoms regularly, yet many don't know how to properly describe them to healthcare providers? Assessment gastrointestinal system I subjective data forms the foundation of diagnosing everything from simple indigestion to serious conditions like Crohn's disease. This systematic approach helps clinicians at places like Mayo Clinic gather crucial patient history through targeted questioning about symptoms, family history, and lifestyle factors. Watch the full video on JoVE Coach to master this concept with expert-led visuals and step-by-step explanations.
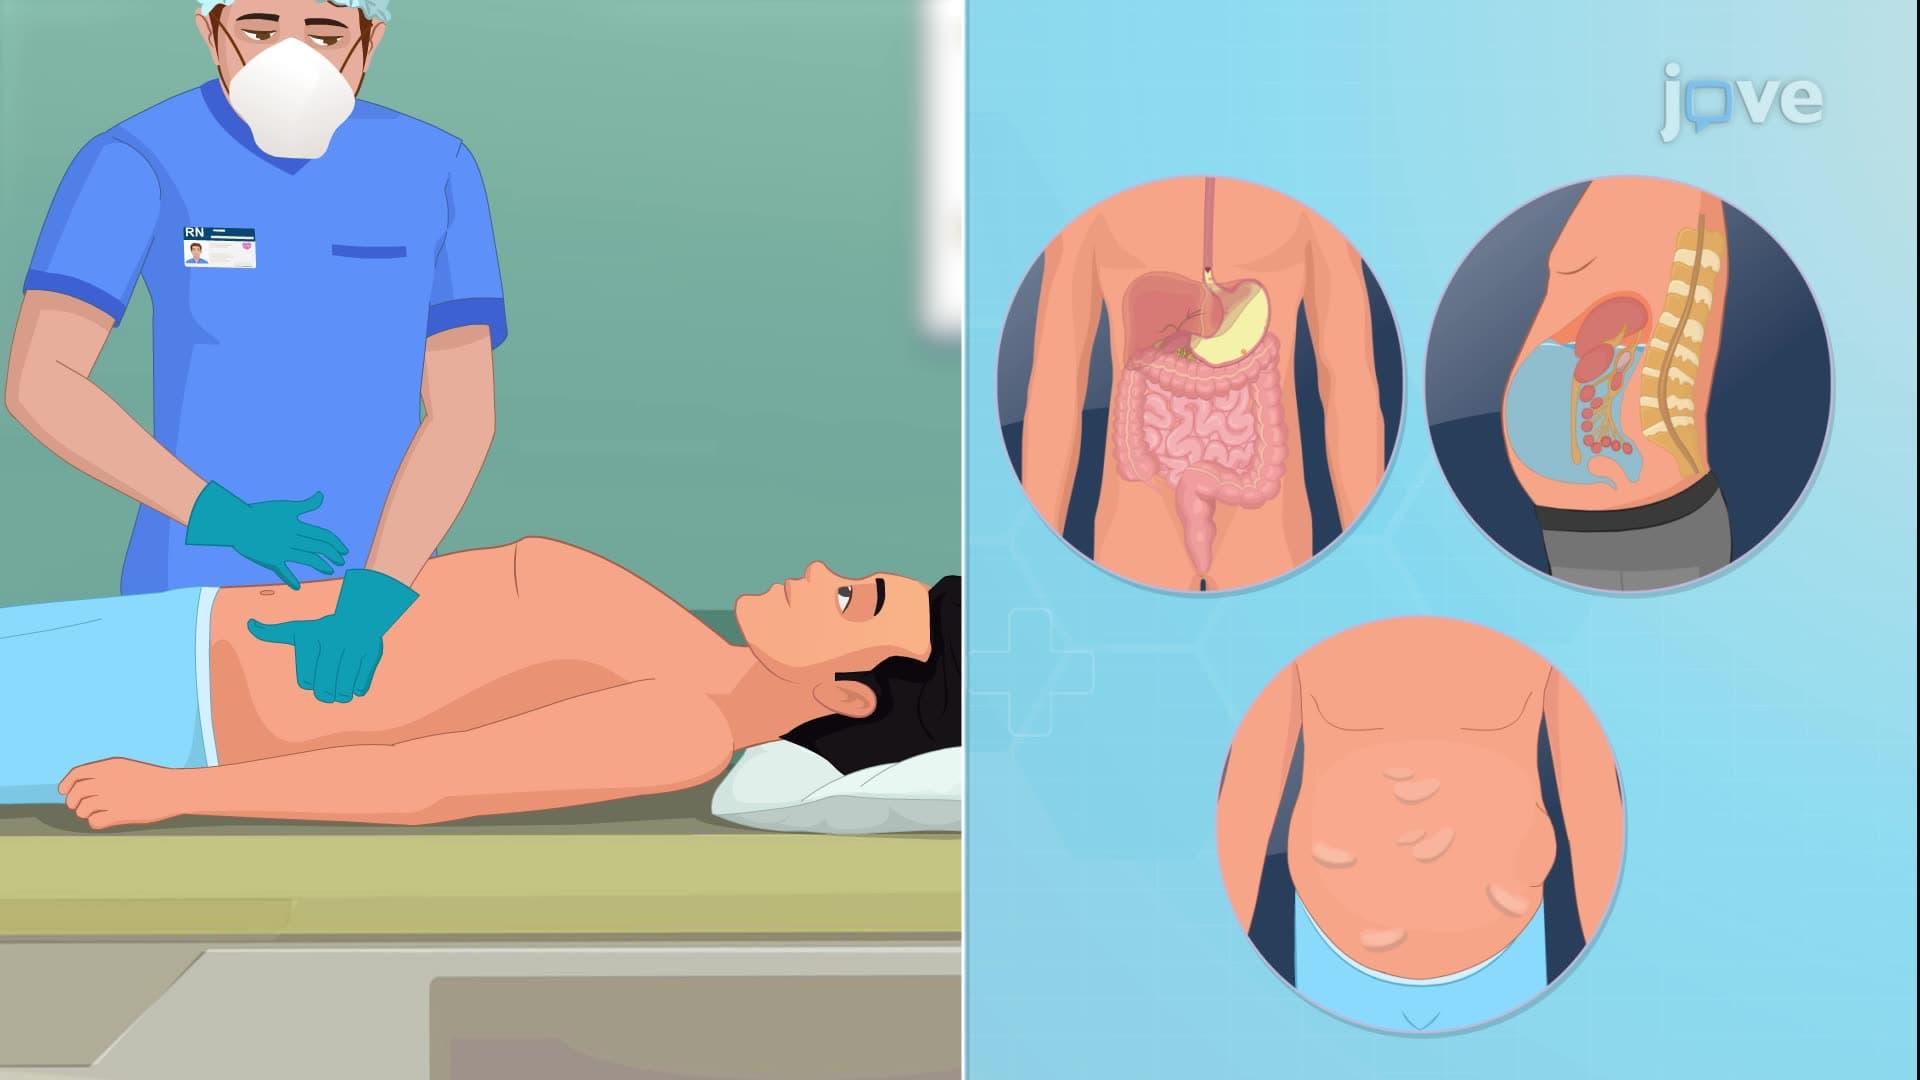
The systematic collection of subjective data forms the cornerstone of gastrointestinal assessment in clinical practice. This comprehensive approach involves structured patient interviews that reveal crucial diagnostic information before any physical examination begins. Healthcare providers at institutions like Johns Hopkins and Cleveland Clinic rely on this methodology to identify potential GI disorders ranging from functional dyspepsia to inflammatory bowel disease.
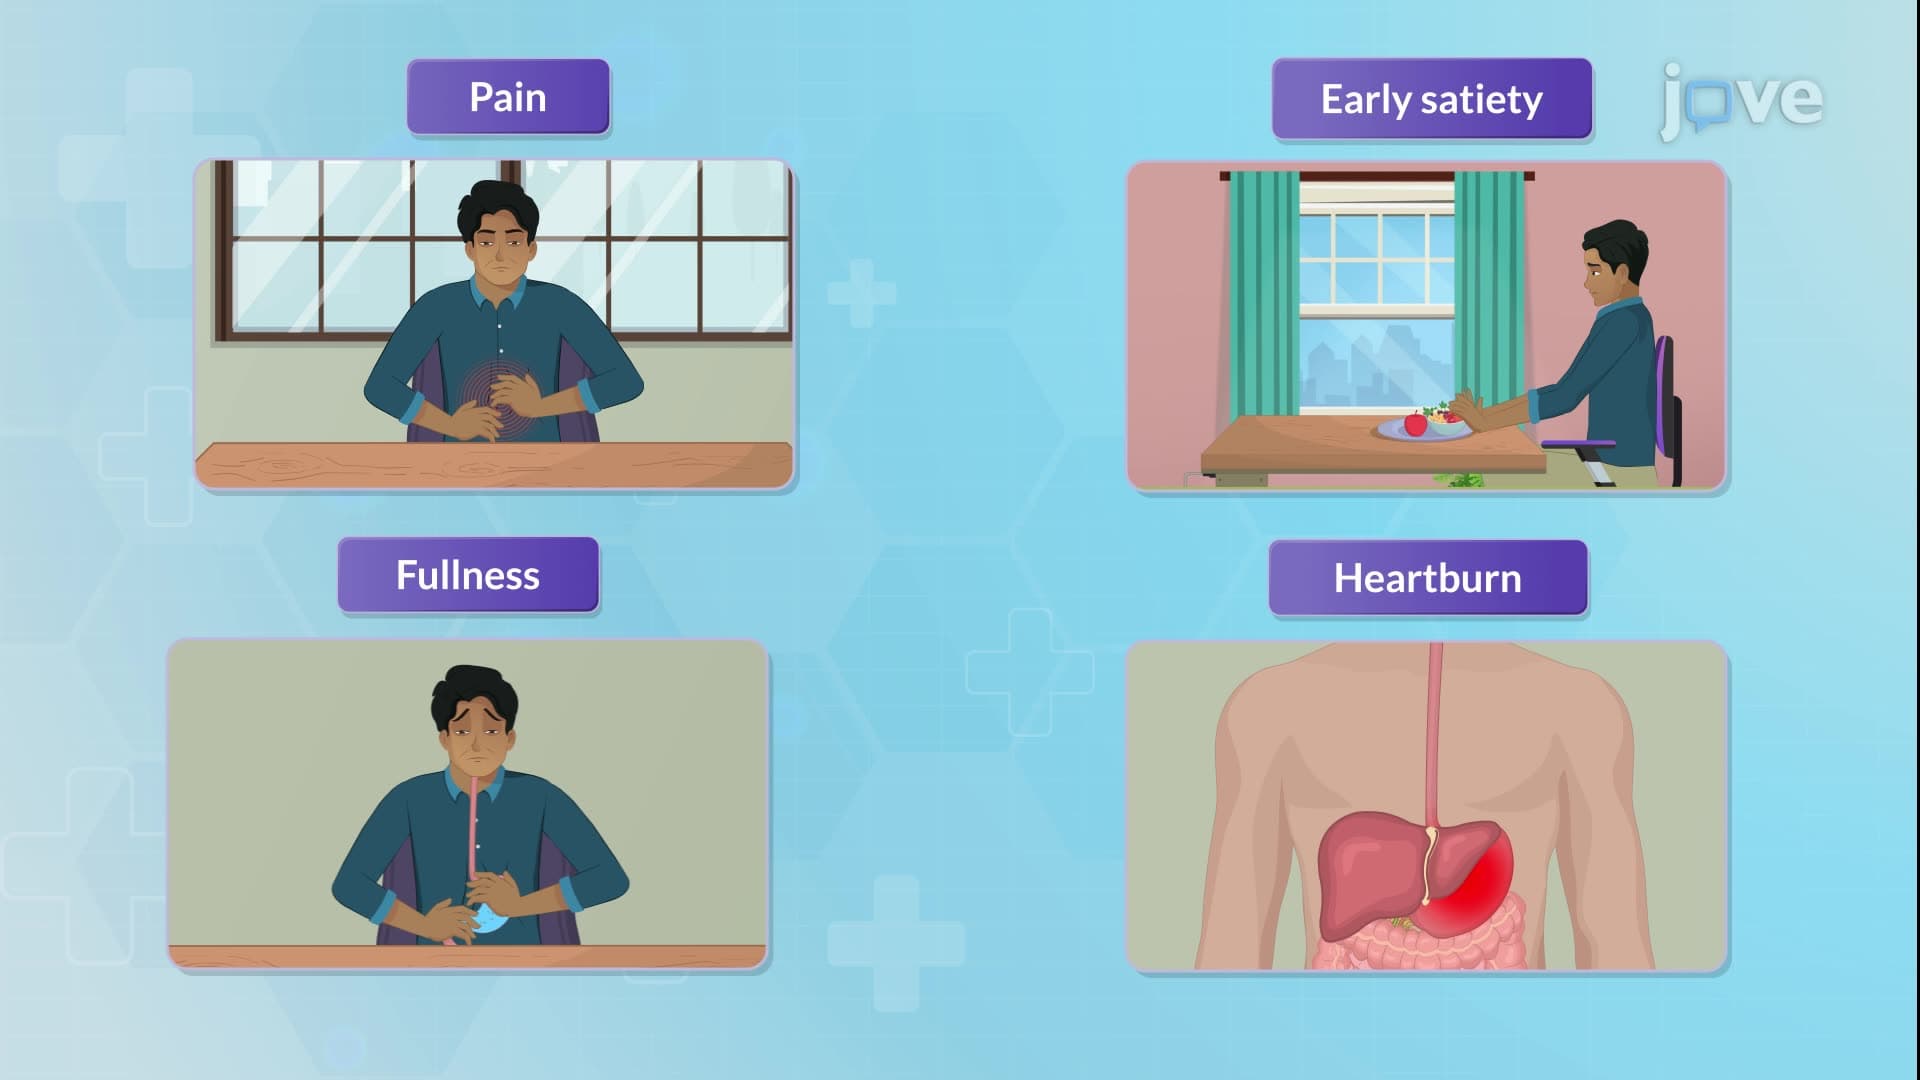
Abdominal pain assessment requires a methodical approach examining multiple characteristics. Location specificity helps narrow differential diagnoses-epigastric pain often suggests peptic ulcer disease, while right lower quadrant pain may indicate appendicitis. Duration patterns distinguish acute conditions (hours to days) from chronic disorders (weeks to months). Character descriptions such as cramping, burning, or stabbing provide additional diagnostic clues. Understanding pain triggers-whether related to meals, position changes, or bowel movements-further refines the clinical picture.
Dyspepsia encompasses a constellation of upper abdominal symptoms including postprandial fullness, early satiety, and epigastric burning. These symptoms affect approximately 25% of the US population annually. Early satiety may indicate gastroparesis or gastric outlet obstruction, while postprandial fullness could suggest functional dyspepsia or peptic ulcer disease. Heartburn symptoms often overlap with gastroesophageal reflux disease (GERD), requiring careful differentiation through detailed questioning about timing and triggers.
Normal bowel patterns vary significantly among individuals, making baseline establishment crucial. Changes in frequency, consistency, or associated symptoms provide valuable diagnostic information. The Bristol Stool Chart serves as a standardized reference for stool consistency assessment. Rectal bleeding requires immediate attention and careful characterization-bright red blood suggests lower GI sources like hemorrhoids or colorectal cancer, while melena indicates upper GI bleeding. This knowledge proves essential for MCAT preparation and clinical rotations in medical school.
Understanding medication impacts on gastrointestinal function completes the subjective assessment. Nonsteroidal anti-inflammatory drugs (NSAIDs) commonly cause peptic ulcers, while opioids frequently result in constipation. Antibiotics may disrupt normal gut flora, leading to antibiotic-associated diarrhea or Clostridioides difficile infection.
Related Micro-courses