Loading video…


 14 Concepts
 6.5K views


Video Summary: Acute Pancreatitis Ii Clinical Manifestations Explained
Did you know that pancreatic pain can be so severe it's often mistaken for a heart attack in emergency rooms across the United States? Acute pancreatitis ii clinical manifestations include intense upper abdominal pain radiating to the back, nausea, and elevated digestive enzymes. At Houston Methodist Hospital, doctors use specific diagnostic criteria combining pain assessment, blood tests, and imaging to identify this life-threatening condition. Watch the full video on JoVE Coach to master this concept with expert-led visuals and step-by-step explanations.
Acute pancreatitis represents one of the most diagnostically challenging gastrointestinal emergencies in American healthcare systems. The clinical presentation creates a complex puzzle that medical students and healthcare professionals must master to provide life-saving interventions. Unlike simple abdominal pain, acute pancreatitis manifests as a multi-system inflammatory response that can rapidly progress from moderate discomfort to life-threatening organ failure.
The American College of Gastroenterology established three cornerstone criteria for diagnosing acute pancreatitis. First, patients experience severe epigastric pain that characteristically radiates to the back, often described as a "boring" sensation that worsens with movement. Second, serum amylase and lipase levels rise significantly-lipase being more specific and remaining elevated longer than amylase. Third, imaging studies reveal pancreatic abnormalities including edema, fluid collections, or necrotic tissue.
Laboratory abnormalities extend beyond pancreatic enzymes. Hypertriglyceridemia often exceeds 1000 mg/dL in severe cases, while hyperglycemia reflects compromised insulin production. Hypocalcemia, particularly concerning when below 8.0 mg/dL, indicates fat necrosis and correlates with severity. Elevated liver enzymes and bilirubin suggest biliary obstruction, helping clinicians identify gallstone-induced pancreatitis-the leading cause in American patients.
The pain pattern in acute pancreatitis follows predictable characteristics that appear frequently on MCAT and USMLE examinations. Patients typically describe sudden-onset, knife-like upper abdominal pain that peaks within hours. The pain classically improves when patients lean forward or assume a fetal position, distinguishing it from peptic ulcer disease or myocardial infarction.
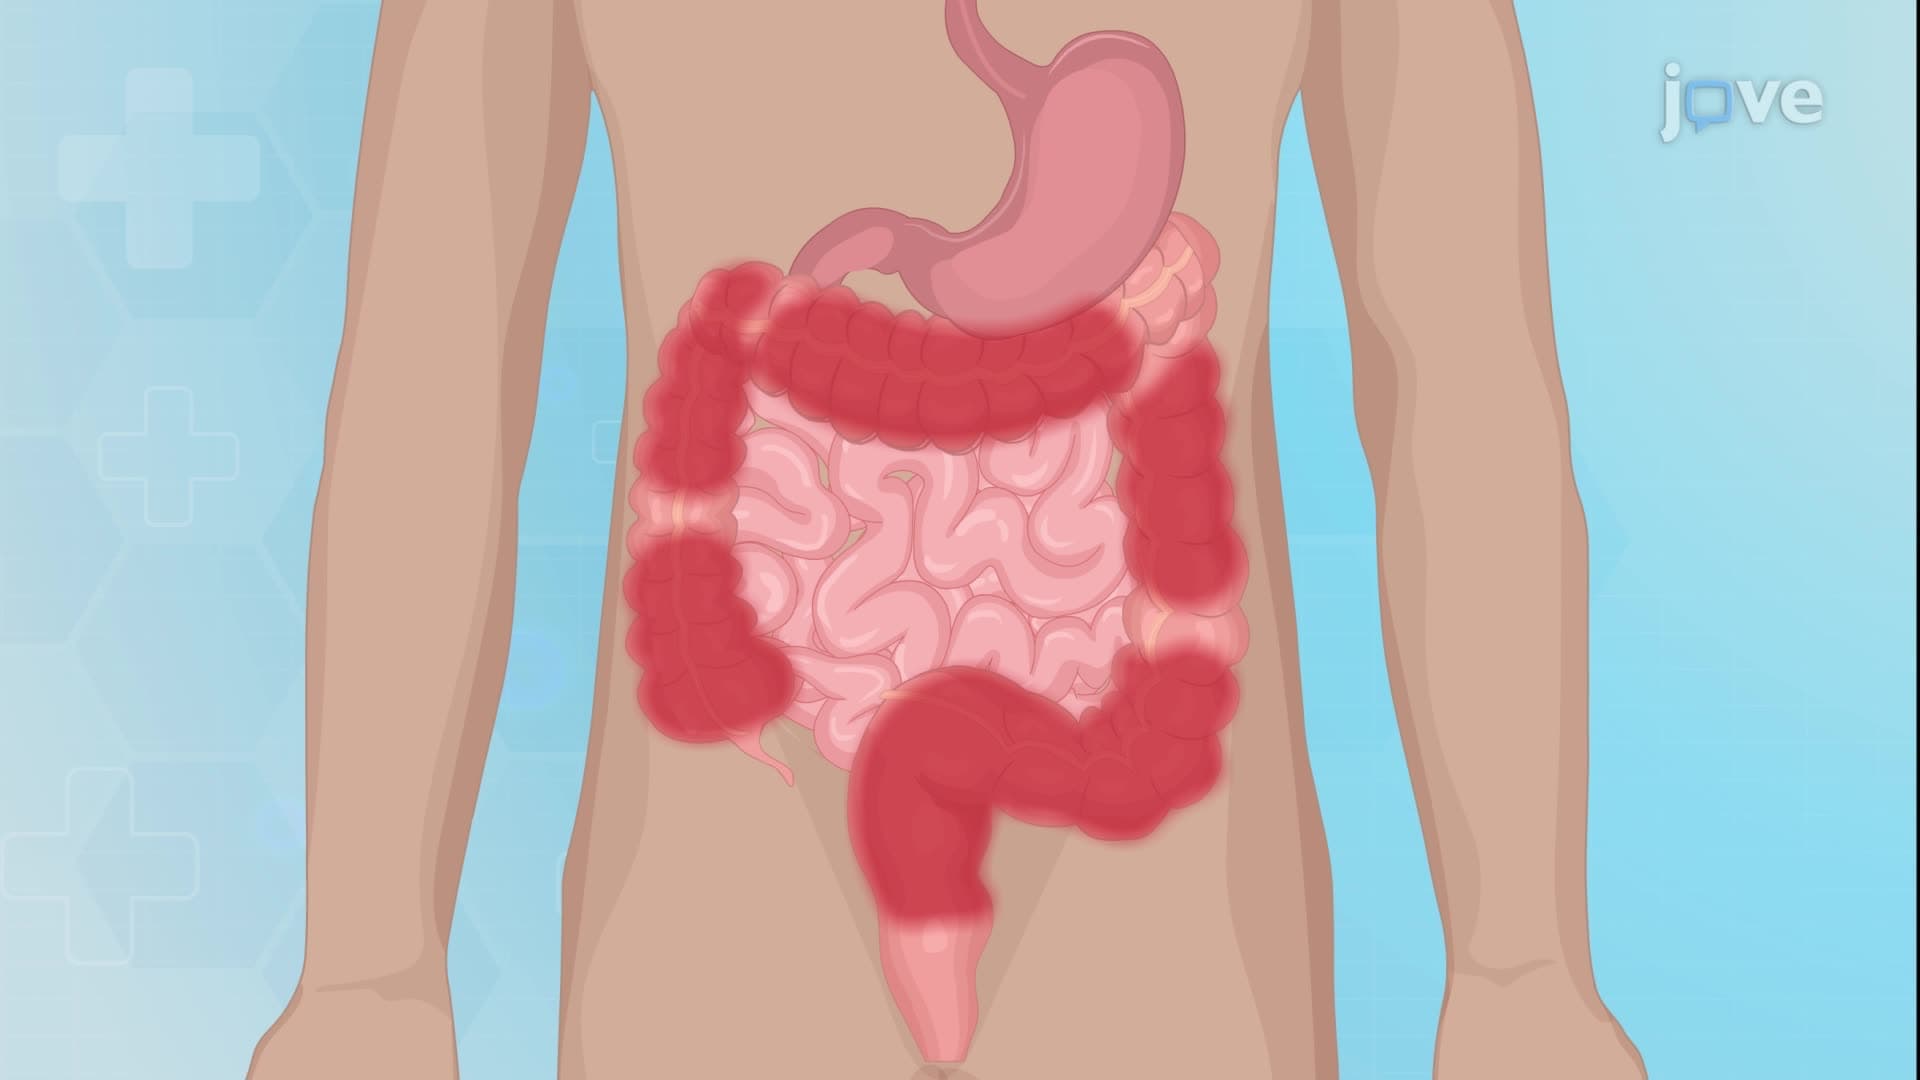
Systemic manifestations reflect the inflammatory cascade. Nausea and vomiting occur in 90% of patients, often triggered by fatty food consumption. Abdominal distention results from ileus, while low-grade fever indicates inflammatory response. Dyspnea may signal pleural effusions or acute respiratory distress syndrome (ARDS). Jaundice, when present, suggests biliary obstruction requiring urgent intervention.
Evidence-based management focuses on supportive care and complication prevention. The NPO (nothing by mouth) protocol allows pancreatic rest, while early enteral feeding within 48-72 hours prevents bacterial translocation. Pain management typically requires parenteral opioids, though morphine is avoided due to sphincter of Oddi spasm concerns.
Fluid resuscitation becomes critical as patients can lose several liters into the retroperitoneal space. Intensive care monitoring includes hemodynamic assessment, blood glucose control, and antibiotic administration for confirmed infections. Understanding these management principles proves essential for nursing students preparing for NCLEX examinations and medical students facing clinical rotations at major teaching hospitals like Johns Hopkins or Mayo Clinic.
Related Micro-courses